FDA approves the Mounjaro cardiovascular indication
FDA approved Mounjaro for reducing heart attack, stroke and cardiovascular death risk in adults with type 2 diabetes, and separately dropped the label language barring the 2.5 mg dose from being used for blood sugar control.
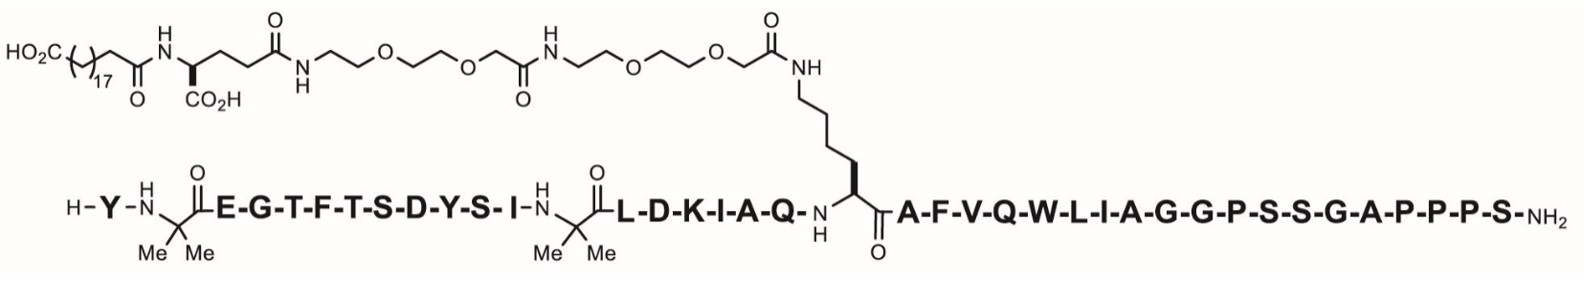
The FDA approved two supplements to Eli Lilly's Mounjaro (tirzepatide) application on August 27, 2026: one adding a cardiovascular indication, and one changing how the lowest dose can be used [1][3]. Lilly announced the cardiovascular approval publicly the next day [5].
The new indication, covered by supplement S-044, is "to reduce the risk of major adverse cardiovascular (CV) events (CV death, non-fatal myocardial infarction, or non-fatal stroke) in adults with type 2 diabetes mellitus who are at high risk for these events" [3][4]. Mounjaro's existing indication — as an adjunct to diet and exercise to improve glycemic control in adults and children 10 and older with type 2 diabetes — remains [4].
What the trial showed
The approval rests on SURPASS-CVOT (trial I8F-MC-GPGN), which FDA's approval letter describes as comparing tirzepatide against dulaglutide on major adverse cardiovascular events in type 2 diabetes [3]. According to Lilly, the trial randomized 13,299 participants 1:1 across 640 sites in 30 countries to Mounjaro (15 mg or the maximum tolerated dose) or Trulicity (dulaglutide) 1.5 mg, both once weekly, in adults with type 2 diabetes and established atherosclerotic cardiovascular disease [5].
Over a median follow-up of 210.1 weeks — about four years — Mounjaro was non-inferior to dulaglutide for three-part MACE, with an 8% lower rate of cardiovascular death, heart attack or stroke and an estimated hazard ratio of 0.92 (95.3% CI: 0.83, 1.01) [5]. Lilly states plainly that "superiority to dulaglutide was not established" [5]. That confidence interval crosses 1.0, meaning the difference between the two drugs was not statistically conclusive.
The same supplement also changed the warnings section on diabetic retinopathy complications in patients with a history of diabetic retinopathy, based on SURPASS-CVOT [3]. The label now directs clinicians to monitor those patients for progression [4]. FDA waived the pediatric study requirement for the cardiovascular indication because the condition "rarely or never occurs in pediatric populations" [3].
The quieter change: the 2.5 mg dose
Supplement S-045 is smaller but more practical. FDA's letter says it "updates the Mounjaro PI to indicate that the 2.5 mg dose of tirzepatide can be used for ongoing glycemic control in patients with type 2 diabetes mellitus" [3].
In the 8/2026 revision, the dosing section reads: "The recommended starting dosage of MOUNJARO is 2.5 mg injected subcutaneously once weekly" and "If additional glycemic control is needed, increase the dosage in 2.5 mg increments after at least 4 weeks on the current dose" [4]. Gone is the earlier statement that the 2.5 mg dosage was for treatment initiation only and not intended for glycemic control, and the label no longer directs an automatic step up to 5 mg after four weeks [4]. Escalation is now framed as conditional — only if more glucose control is needed. The maximum is unchanged at 15 mg weekly in adults and 10 mg weekly in patients 10 and older [4].
These two supplements apply to Mounjaro, NDA 215866 [1]. The documents provided here do not address Zepbound, the tirzepatide product approved for weight management, so any parallel change to that label is not established by these sources.
Why it matters for patients
For adults with type 2 diabetes at high cardiovascular risk, an FDA-approved indication is what insurers, formularies and prescribing guidelines typically look for. Mounjaro now carries that language on its label alongside dulaglutide, which already had it [5]. The evidence base is a head-to-head comparison, not a placebo trial, so the finding is that Mounjaro was not worse than an established option — not that it was better [5].
The 2.5 mg change may matter more day to day. Some people get meaningful A1C control at the starting dose, or cannot tolerate higher ones because of nausea, vomiting or diarrhea — the most common adverse reactions reported in at least 5% of patients [4]. The prior wording made staying at 2.5 mg look like off-label use, which could complicate refills or coverage. That barrier is now gone from the label [3][4]. Decisions about dosing remain between a patient and their prescriber.
What happens next
Lilly submitted the two applications on October 27 and November 5, 2025 [3]. Under the approval letter, Lilly had 14 days from August 27 to submit updated labeling content, and must promptly revise promotional materials to match [3]. The updated prescribing information is already posted on DailyMed, dated August 27, 2026 [2]. Lilly says regulatory submissions based on SURPASS-CVOT are under review in additional markets, and the data is already in Mounjaro's European product information [5].
Sources
- https://www.accessdata.fda.gov/scripts/cder/daf/index.cfm?event=overview.process&ApplNo=215866
- https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d2d7da5d-ad07-4228-955f-cf7e355c8cc0
- https://www.accessdata.fda.gov/drugsatfda_docs/appletter/2026/215866Orig1s044,215866Orig1s045ltr.pdf
- https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/215866s044s045lbl.pdf
- https://investor.lilly.com/news-releases/news-release-details/fda-approves-lillys-mounjaro-tirzepatide-reduce-cardiovascular
- https://www.prnewswire.com/news-releases/fda-approves-lillys-mounjaro-tirzepatide-to-reduce-cardiovascular-risk-in-adults-with-type-2-diabetes-302862415.html
Semaglutides.org is for information only and is not medical advice. Always talk to a licensed healthcare provider about your own care. Some links to telehealth services are affiliate links, labeled where they appear.