Study describes tirzepatide as an imbalanced dual GIP and GLP-1 receptor agonist
Laboratory work explains why tirzepatide acts differently at its two target receptors, but it is not a new trial result and reports nothing about safety.
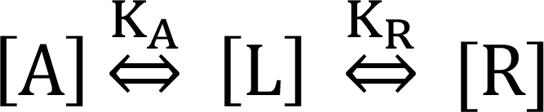
Tirzepatide, an experimental drug for type 2 diabetes and obesity, acts differently at its two target receptors, according to a study published in JCI Insight. The authors describe it as an "imbalanced and biased" dual agonist: it engages the GIP receptor more than the GLP-1 receptor, and at the GLP-1 receptor it pushes one signaling route over another [1].
The work comes from researchers at Eli Lilly and Company, Duke University and the University of Copenhagen, and appeared in the journal's September 3, 2020 issue as JCI Insight 5(17):e140532 [1][2]. The paper was accepted July 22, 2020 [1]. At the time, tirzepatide, also called LY3298176, was under development for type 2 diabetes, obesity and nonalcoholic steatohepatitis [1].
The team first set out a method for calculating how much of each receptor the drug occupies at doses that had produced clinical effects. That analysis showed a greater degree of engagement with the GIP receptor than with the GLP-1 receptor, which the authors call an imbalanced mechanism of action [1].
In signaling experiments, tirzepatide mimicked the body's own GIP at the GIP receptor. At the GLP-1 receptor it behaved differently from the natural GLP-1 hormone: it favored cAMP generation over beta-arrestin recruitment, and it was weaker than GLP-1 at driving the receptor into the cell, a process called internalization [1]. In experiments using primary islets, beta-arrestin1 limited the insulin response to GLP-1 but not to GIP or tirzepatide. The authors say that suggests the biased signaling of tirzepatide enhances insulin secretion [1].
The paper cites earlier trial results for context. In a 26-week phase 2b trial in type 2 diabetes, about 30% of patients taking the 15 mg dose reached normoglycemia, defined as HbA1c below 5.7% under the American Diabetes Association standard, and 1 in 4 participants lost at least 15% of their body weight [1]. Tirzepatide also lowered fasting triglycerides, and a HOMA2-IR analysis pointed to improved insulin sensitivity that was only partly accounted for by weight loss [1].
Why it matters for patients
This is laboratory work about how a drug interacts with receptors. It is not a new trial result, and it does not report side effects, safety findings or long-term outcomes such as heart, kidney or eye effects.
It does help explain why a medicine that acts on two hormone pathways might behave differently from one that acts only on the GLP-1 receptor, which is the kind of question patients and clinicians raise when comparing treatment options. The authors conclude that imbalance toward the GIP receptor, combined with the distinct signaling at the GLP-1 receptor, "may account for" the efficacy seen so far in trials [1]. That is a hypothesis about mechanism, not proof of better results for patients.
Tirzepatide is described in the paper as an investigational agent [1]. Nothing in the study establishes that it is safer or more effective than any approved drug, and it contains no dosing guidance. The 15 mg figure is a dose used in a phase 2b trial, not a recommendation [1].
What happens next
The paper does not disclose what further trials were planned or when results were expected. It notes only that the drug was under development at the time of publication [1]. Whether these signaling findings translate into measurable differences in patient outcomes has not been reported in these sources.
Sources
Semaglutides.org provides information only, not medical advice. Talk to a licensed provider about your own care before making changes. Some telehealth links are affiliate links and are labeled where they appear.